Clean FRCS notes with inline figures
Clinical photo showing patient with asymmetrical scapula
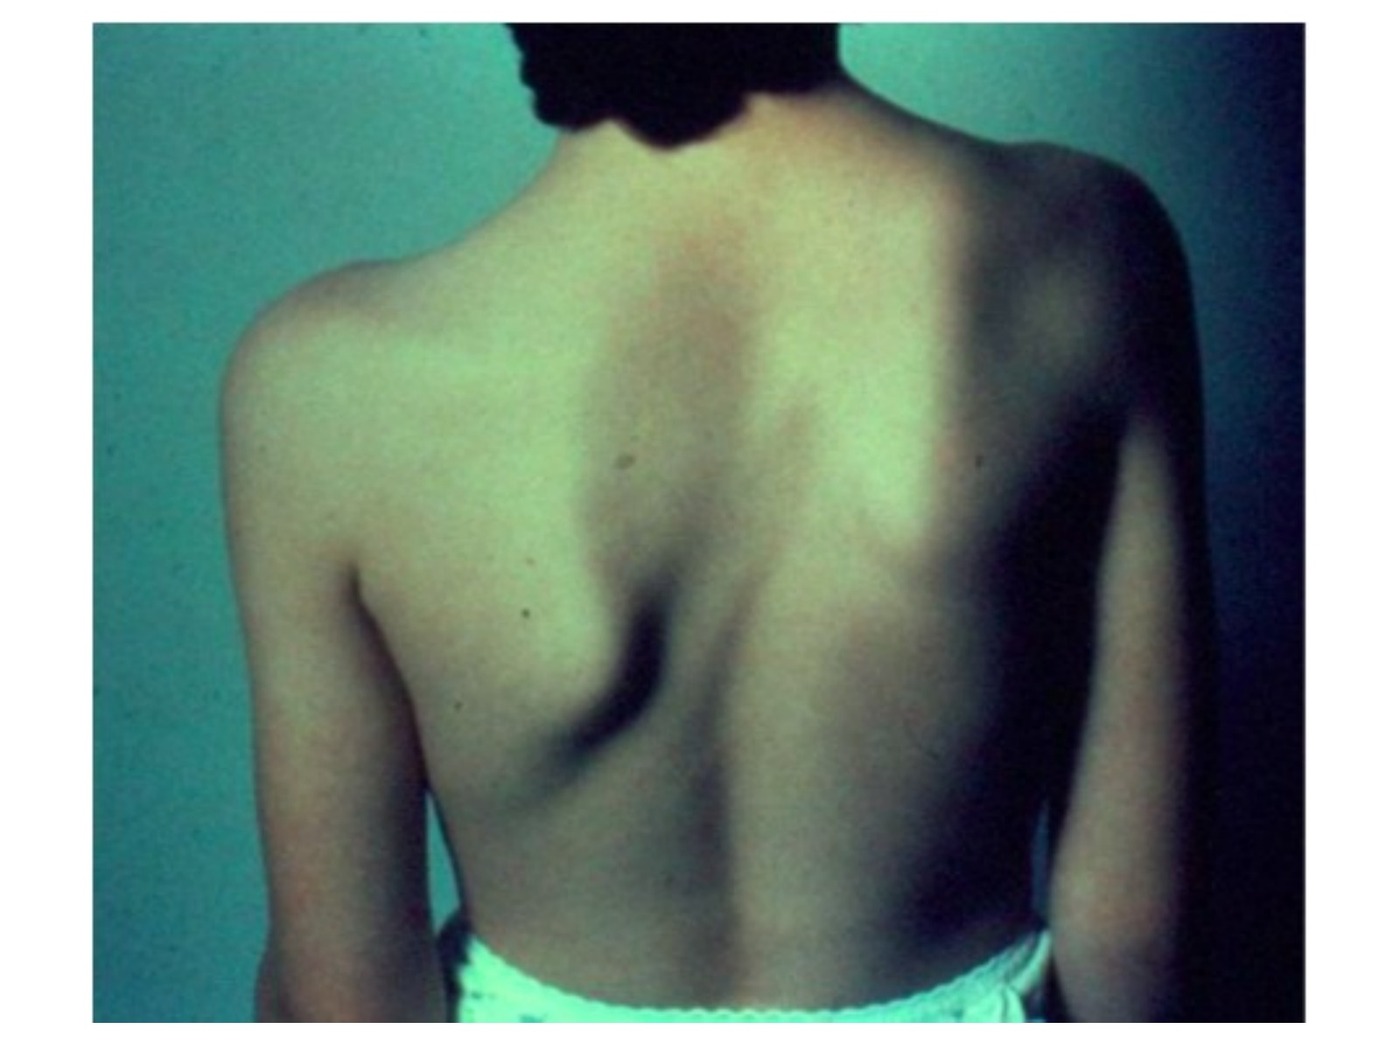
•Right sided scapula is hypoplastic and undescended
•Hairline also appears low
•Short webbed neck
•No scapular winging
•Also look from the front to see if there is upward tilting of clavicle
•This is a Sprengel shoulder
Associations:
•1. Klippel Feil syndrome
•2. Congenital scoliosis
•3. Cervical spinal bifida
•4. VACTERL +/- situ invertus
Examination
•Neck: Short, stiff
•Document omovertebral bar, shoulder movement, abduction power (medial wing + superomedial angle move superiorly → glenoid pointed inferiorly)
•Shoulder abduction: movement only coming from GHJ, no STJ movement
•Look for UL abnormalities (VACTERL), periscapular muscle fibrosis / weakened, check distal NV status (syringomyelia)
•Look for scoliosis/ kyphosis/ back pitting (spina bifida)
Xray
•Omovertebral bar (bar best seen on lateral/ oblique Xray of C spine)
•Clavicle uptilt
•High riding scapula
•Small scapula (Transverse > vertical)
•Inferomedial corner medial tilt + glenoid downward tilt
•Association with Klippel Feil: C spine failure of segmentation, C1/2 instability, Cranial settling
•Need CT and MRI spine to look for bar and spinal problem such as dural ectasia or diastematomyelia
•Also cardiac and renal workup, also rule out other C spine problems
Staging:
•Caverndish
•Very mild, not detectable in clothing
•Mild 1-2cm higher
•Moderate 2-5cm higher
•Severe >5cm higher (superior angle near occiput)
Management
•OT if 1. Cosmetic problem, 2. Abduction < 120 @ 3-8yo (too late more nerve injury)
Aims:
•1. Excise omovertebral bar + superior trapezius release at C4
•2. Relocation of scapula
•Woodward (detachment and distal advancement of the midline origin of parascapular muscles)
•Green (extraperiosteal detachment of periscapular muscle, then hold the scapula in its new position with spring wire traction and spica casting for 3 weeks)
•Both improve 50deg
•3. Clavicle morselized osteotomy → preserve periosteum (decrease brachial plexus injury)
•→ Principle is to improve shoulder abduction (will improve 30 deg, Caverndish by 1 grade)
•Congenital undescended scapula
•From 4-6th C spine (pharyngeal arch), caudal migration to T2-7 during 9th to 12th weeks of gestation
Interruption of embryonic subclavian blood supply
•10-30% bilateral
•Present in 1/3 Klippel-Feil
•Association: scoliosis, spinal dysraphism, VACTERL
•Klippel Feil Syndrome (SGM 1 gene at chromosome 8)
•Congenital condition with fusion of more than two cervical vertebra
Classical Triad
•Low posterior hair line
•Short webbed neck
•Decreased cervical movement (normal F/E, decrease side bending)
•(Hearing loss, micrognathia, torticollis, scoliosis)
Xray triad
•Unsegmented cervical spine (commonest C2/3)
•ADI, C1/2 instability
•Adjacent segment degeneration
•(may also have basilar invagination)
•If involve C2 → no contact sports
•If lower → usually asymptomatic, until adjacent levels degenerate (100%)→ contact sports ok
•OT if 1. pain, 2. instability, 3. neurology
•Check/perform check CVS system and urogenital system before OT