Clean FRCS notes with inline figures
Open reduction
•Anterior vs medial
Anterior:
Absolute indications
•High and chronic dislocations, femoral head stuck to ilium (>1-1.5yo)
•Perform capsulorrphahy for very unstable hips
•Plan acetabuloplasty
Adv:
•Good exposure (easier in sizable child)
•Can do capsulorrhaphy
•Can reduce highly dislocated hip
Disadv:
•Large wound, more bleeding
•Iliac crest apophysis and hip abductor at risk
•LCFN at risk
Key steps:
•Bikini incision +/- extend proximal along iliac crest
•Protect LCFN
•Plane between sartorius and TFL
•+/- Split iliac apophysis and release glut med from outer table
•Plane between rectus and glut med
•Detach and tag straight head and reflected head of rectus
•Psoas tendon lengthening at the pelvic brim
•T capsulotomy, acetabular based
•Excision of intraarticular obstacles to reduction (ligamentum teres, pulvinar)
•+/- acetabular / femoral osteotomy
•Capsulorrhaphy
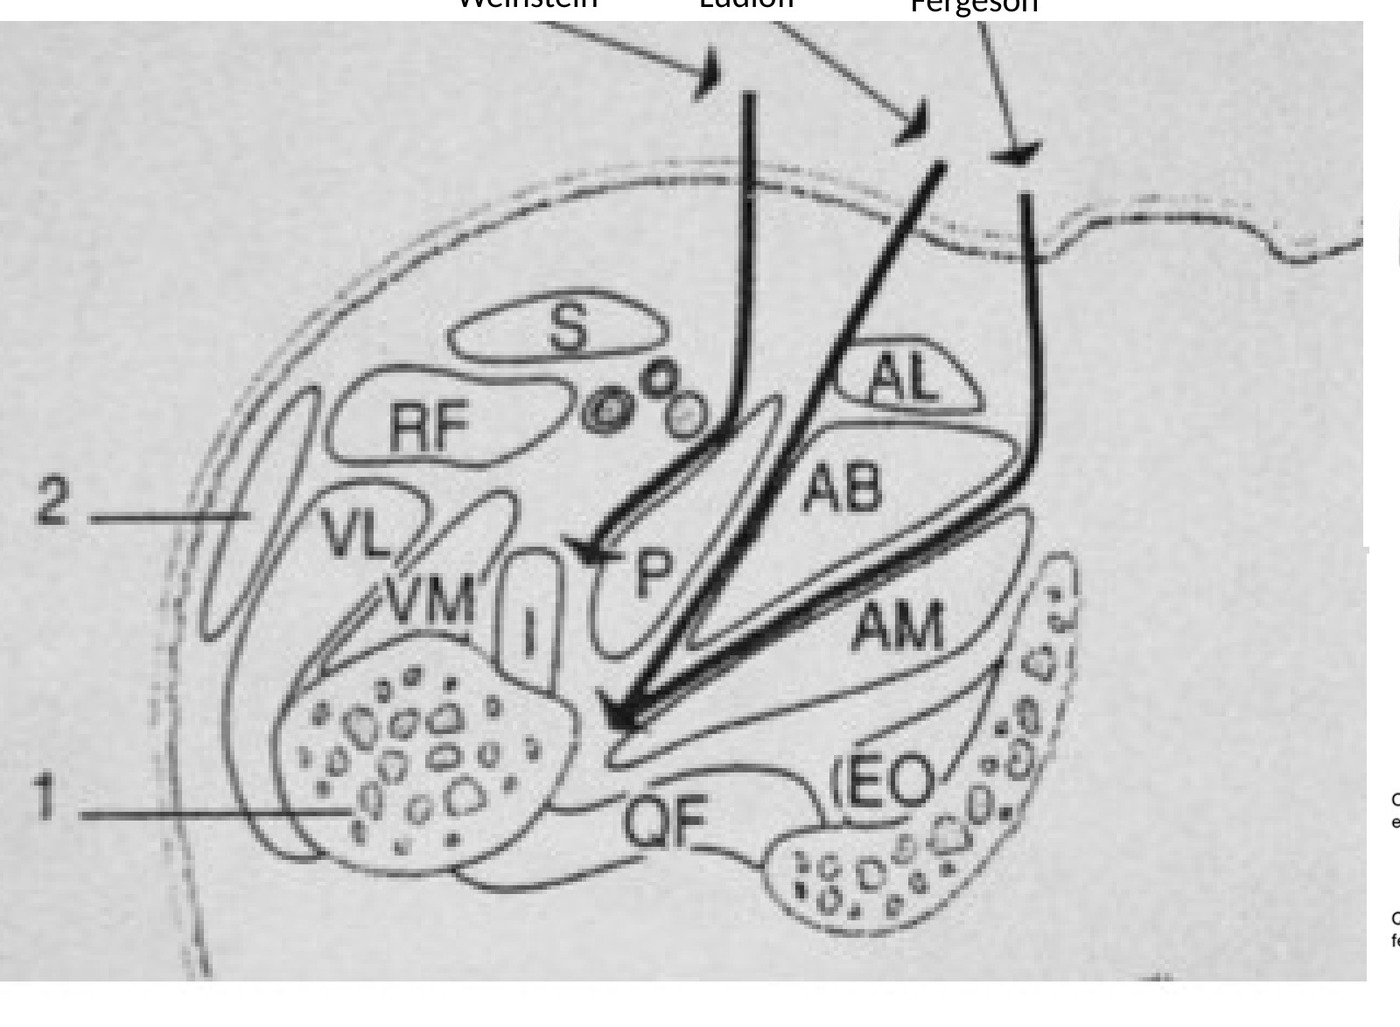
Medial (Weinstein / Ludloff / Ferguson):
•Abs c/i (~>18mo)
Adv:
•Small wound and less bleeding
•Can deal with some of the pathology (iliopsoas, transverse acetabular ligament)
•Avoid stripping of iliac apophysis and abductors
•Adductor tenotomy through same incision
Disadv:
•Risk of injury to MCFA → AVN
•Cannot perform capsulorrhaphy
•Obturator nerve injury
•Ant div supply gracilis, adductor longus, adductor brevis, lies on add brevis
•Post div supply add magnus, lies on add magnus
•(Ischial portion of add magnus supply by sciatic n)
•Not for open reduction within 6mth
How to do medial approach
•GA (usually children), supine, affected limb in abduction, flexion and ER
•Landmark: 3cm below pubic tubercle (attachment of adductor longus)
•Incision: longitudinal just below pubic tubercle and along adductor longus
Dissection plane:
•Weinstein = between NVB and pectineus (best to reach labrum as the pectineus is not in the way, surgical landmark will be the anterior obturator nerve)
•Ludloff = between pectineus and AB
•Ferguson = between AL and G, then AB and AM
•Adductor tendon release as necessary
•Palpate lessor tuberosity, release iliopsoas (care to protect MCFA)
•Capsulotomy, acetabular based
•Release ligamentum teres, pulvinar
•If go superficial to pectineus (Weinstein), can approach superior aspect of hip joint also
Structure at risk:
•Obturator nerve (anterior branch of obturator nerve between adductor longus and brevis → injury causing adductor contracture)
•Medial circumflex femoral artery (near psoas tendon, need direct vision when performing tenotomy, do capsulotomy close to acetabulum)
•External pudendal artery (superficial to pectineus)
•Femoral vessels (Weinstein)
•Innervation of medial compartment
•Adductor magnus: posterior branch of obturator nerve + tibial nerve
•Others by anterior branch of obturator nerve