FRCS Paediatric Ortho — improved notes
FRCS Paediatric Ortho — visual inline notes

051. Chronic osteomyelitis

visual-inline rebuild1 extracted figuresspeaker notes XML50 study lines3 Q&A

Individual slide images have been cropped from the rendered slide and inserted beside the matching note section. The full slide remains below only for layout/audit.

Clean FRCS notes with inline figures

Chronic:

•Aim: control infection, look for complication, skeletal stabilisation if pathological fracture

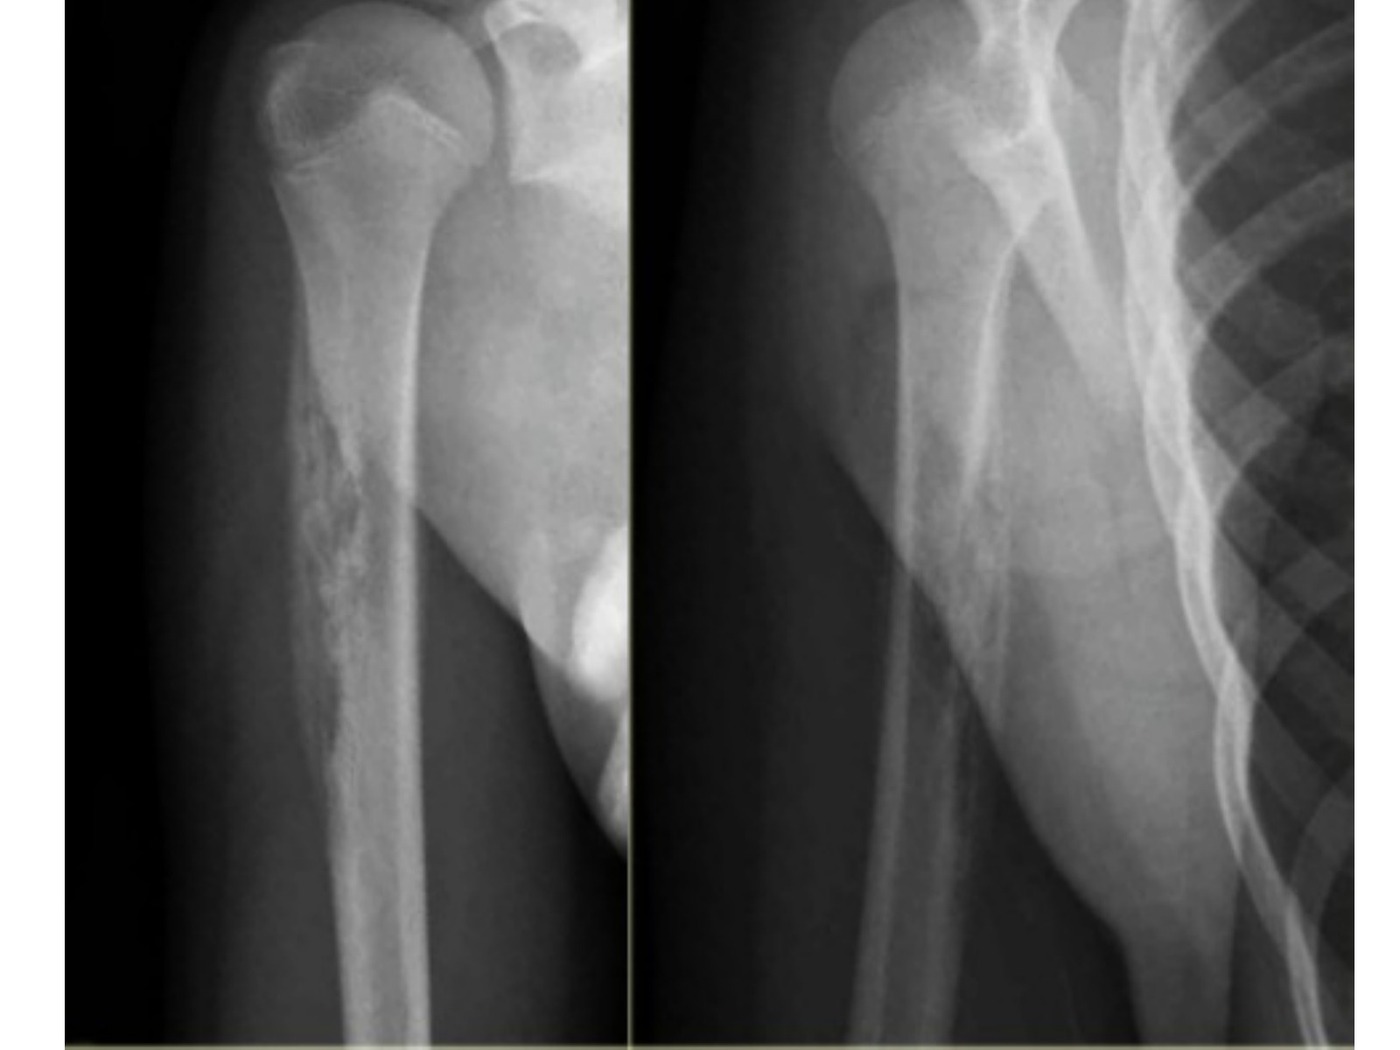
Radiographic description

•Bone destruction at proximal shaft involving half of diameter on both AP/ lat
•Clinically discharging sinus over arm
•With Hx of previous acute osteomyelitis likely chronic osteomyelitis

Assessment:

•PE: skin and soft tissue condition
•Blood: WBC, CRP, ESR
•CT to look for collection
•Common bacteria: S aureus, polymicrobial

Cierny classification

•I Intramedullary → Deroof bone for IM debridement (IM reaming if skeletally matured)
•II Superficial (bone surface) → Debridement of cortex till paprika sign, may need soft tissue coverage
•III Localized (cortex + medullary) → Saucerization, debridement, antibiotic bead +/- ex fix and flap
•IV Diffuse → + Ex fix, debridement, flap
•A/B/C host immunity
•Eradication of infection (3)
•1. Debridement
•Saucerization and sequestrectomy, until healthy bleeding (paprika sign)
•Dead space management by antibiotic loaded cement spacer / gentamicin beads / VAC dressing
•2. Antibiotics: local abx loaded cement and systemic antibiotics
•3. +/- skeletal stabilization (depends on Cierny staging)
•Repeated debridement till clean

Mx of bone defect:
Ultrasound image
Fig 1. Ultrasound imagetop left
•Small <4cm: Papineau (open bone grafting) / autologous cancellous bone graft / bypass graft (cross union of T/F)
•Large > 6cm: Masquelet technique, vascularized bone graft, bone transport / distraction osteogenesis (new: bi/trifocal bone transport to reduce time to distraction and consolidation but bone maturation time is longer)
•Papineau technique (open bone grafting)
•Bed free of infection with health granulation tissue (blood supply)
•Lay down a layer of morselized bone graft on defect not thicker than 2 cm, gradually taken up and form granulation tissue, then add another layer of bone graft
•Leaving the graft exposed beneath a non-adherent dressing
•Continue till dead space obliterated and bone graft well covered by granulation tissue
•Then go for Vacuum assisted closure +/- Split thickness skin graft

Use of VAC:

•Remove chronic oedema
•Enhance blood flow
•Promote granulation tissue at floor
•Final soft tissue coverage
•Soft tissue reconstruction ladder
•May need local or distant muscle flap for coverage
•Adequate soft tissue coverage with vascularity help resolution of osteomyelitis

•Chronic recurrent multifocal osteomyelitis
•Rare
•Young female
•Periods of exacerbation and remission
•Clavicle, sternum, tarsals, rib, spine

Culture negative, pathology only lymphocytic infiltrate

Ddx: Ewing, OO, subacute osteomyelitis

•NSAIDs prn, usually self limiting and resolve after adulthood

Direct Q&A

Q1 What are the radiographic findings for Chronic osteomyelitis?
•Bone destruction at proximal shaft involving half of diameter on both AP/ lat
•Clinically discharging sinus over arm
•With Hx of previous acute osteomyelitis likely chronic osteomyelitis
Q2 What assessment points are listed for Chronic osteomyelitis?

PE: skin and soft tissue condition

•Blood: WBC, CRP, ESR
•CT to look for collection
•Common bacteria: S aureus, polymicrobial
Q3 How is Chronic osteomyelitis classified here?
•I Intramedullary → Deroof bone for IM debridement (IM reaming if skeletally matured)
•II Superficial (bone surface) → Debridement of cortex till paprika sign, may need soft tissue coverage
•III Localized (cortex + medullary) → Saucerization, debridement, antibiotic bead +/- ex fix and flap
•IV Diffuse → + Ex fix, debridement, flap
•A/B/C host immunity
•Eradication of infection (3)
•1. Debridement
•Saucerization and sequestrectomy, until healthy bleeding (paprika sign)
•Dead space management by antibiotic loaded cement spacer / gentamicin beads / VAC dressing
•2. Antibiotics: local abx loaded cement and systemic antibiotics
•3. +/- skeletal stabilization (depends on Cierny staging)
•Repeated debridement till clean

Raw speaker-note hierarchy audit

#lvlmarLindentlogicaloriginal note line
10NoneNone0Chronic:
20NoneNone0Aim: control infection, look for complication, skeletal stabilisation if pathological fracture
30NoneNone0Describe Xray:
40NoneNone0Bone destruction at proximal shaft involving half of diameter on both AP/ lat
50NoneNone0Clinically discharging sinus over arm
60NoneNone0With Hx of previous acute osteomyelitis likely chronic osteomyelitis
70NoneNone0Assessment:
80NoneNone0PE: skin and soft tissue condition
90NoneNone0Blood: WBC, CRP, ESR
100NoneNone0CT to look for collection
110NoneNone0Common bacteria: S aureus, polymicrobial
120NoneNone0Cierny classification
131NoneNone1I Intramedullary → Deroof bone for IM debridement (IM reaming if skeletally matured)
141NoneNone1II Superficial (bone surface) → Debridement of cortex till paprika sign, may need soft tissue coverage
151NoneNone1III Localized (cortex + medullary) → Saucerization, debridement, antibiotic bead +/- ex fix and flap
161NoneNone1IV Diffuse → + Ex fix, debridement, flap
170NoneNone0A/B/C host immunity
180NoneNone0Eradication of infection (3)
191NoneNone11. Debridement
201628650-1714502Saucerization and sequestrectomy, until healthy bleeding (paprika sign)
211628650-1714502Dead space management by antibiotic loaded cement spacer / gentamicin beads / VAC dressing
221NoneNone12. Antibiotics: local abx loaded cement and systemic antibiotics
231NoneNone13. +/- skeletal stabilization (depends on Cierny staging)
240NoneNone0Repeated debridement till clean
250NoneNone0Mx of bone defect:
261NoneNone1Small <4cm: Papineau (open bone grafting) / autologous cancellous bone graft / bypass graft (cross union of T/F)
271NoneNone1Large > 6cm: Masquelet technique, vascularized bone graft, bone transport / distraction osteogenesis (new: bi/trifocal bone transport to reduce time to distraction and consolidation but bone maturation time is longer)
280NoneNone0Papineau technique (open bone grafting)
290171450-1714501Bed free of infection with health granulation tissue (blood supply)
300171450-1714501Lay down a layer of morselized bone graft on defect not thicker than 2 cm, gradually taken up and form granulation tissue, then add another layer of bone graft
310171450-1714501Leaving the graft exposed beneath a non-adherent dressing
320171450-1714501Continue till dead space obliterated and bone graft well covered by granulation tissue
330171450-1714501Then go for Vacuum assisted closure +/- Split thickness skin graft
340000Use of VAC:
350457200-3048001Remove chronic oedema
360457200-3048001Enhance blood flow
370457200-3048001Promote granulation tissue at floor
380457200-3048001Final soft tissue coverage
390457200-3048001Soft tissue reconstruction ladder
400457200-3048001May need local or distant muscle flap for coverage
410457200-3048001Adequate soft tissue coverage with vascularity help resolution of osteomyelitis
420NoneNone0============================================
430NoneNone0Chronic recurrent multifocal osteomyelitis
440171450-1714501Rare
450171450-1714501Young female
460171450-1714501Periods of exacerbation and remission
470171450-1714501Clavicle, sternum, tarsals, rib, spine
480171450-1714501Culture negative, pathology only lymphocytic infiltrate
490171450-1714501Ddx: Ewing, OO, subacute osteomyelitis
500171450-1714501NSAIDs prn, usually self limiting and resolve after adulthood

Improved semantic hierarchy used for the study notes

#semantic levelsection?rewritten line
10yesChronic:
21Aim: control infection, look for complication, skeletal stabilisation if pathological fracture
30yesRadiographic description
41Bone destruction at proximal shaft involving half of diameter on both AP/ lat
51Clinically discharging sinus over arm
61With Hx of previous acute osteomyelitis likely chronic osteomyelitis
70yesAssessment:
81PE: skin and soft tissue condition
91Blood: WBC, CRP, ESR
101CT to look for collection
111Common bacteria: S aureus, polymicrobial
120yesCierny classification
131I Intramedullary → Deroof bone for IM debridement (IM reaming if skeletally matured)
141II Superficial (bone surface) → Debridement of cortex till paprika sign, may need soft tissue coverage
151III Localized (cortex + medullary) → Saucerization, debridement, antibiotic bead +/- ex fix and flap
161IV Diffuse → + Ex fix, debridement, flap
171A/B/C host immunity
181Eradication of infection (3)
1911. Debridement
202Saucerization and sequestrectomy, until healthy bleeding (paprika sign)
212Dead space management by antibiotic loaded cement spacer / gentamicin beads / VAC dressing
2212. Antibiotics: local abx loaded cement and systemic antibiotics
2313. +/- skeletal stabilization (depends on Cierny staging)
241Repeated debridement till clean
250yesMx of bone defect:
261Small <4cm: Papineau (open bone grafting) / autologous cancellous bone graft / bypass graft (cross union of T/F)
271Large > 6cm: Masquelet technique, vascularized bone graft, bone transport / distraction osteogenesis (new: bi/trifocal bone transport to reduce time to distraction and consolidation but bone maturation time is longer)
281Papineau technique (open bone grafting)
291Bed free of infection with health granulation tissue (blood supply)
301Lay down a layer of morselized bone graft on defect not thicker than 2 cm, gradually taken up and form granulation tissue, then add another layer of bone graft
311Leaving the graft exposed beneath a non-adherent dressing
321Continue till dead space obliterated and bone graft well covered by granulation tissue
331Then go for Vacuum assisted closure +/- Split thickness skin graft
340yesUse of VAC:
351Remove chronic oedema
361Enhance blood flow
371Promote granulation tissue at floor
381Final soft tissue coverage
391Soft tissue reconstruction ladder
401May need local or distant muscle flap for coverage
411Adequate soft tissue coverage with vascularity help resolution of osteomyelitis
420——
431Chronic recurrent multifocal osteomyelitis
441Rare
451Young female
461Periods of exacerbation and remission
471Clavicle, sternum, tarsals, rib, spine
480yesCulture negative, pathology only lymphocytic infiltrate
490yesDdx: Ewing, OO, subacute osteomyelitis
501NSAIDs prn, usually self limiting and resolve after adulthood