FRCS Paediatric Ortho — improved notes
FRCS Paediatric Ortho — visual inline notes

085. Lenke classification

visual-inline rebuild1 extracted figuresspeaker notes XML26 study lines3 Q&A

Individual slide images have been cropped from the rendered slide and inserted beside the matching note section. The full slide remains below only for layout/audit.

Clean FRCS notes with inline figures

Lenke classification
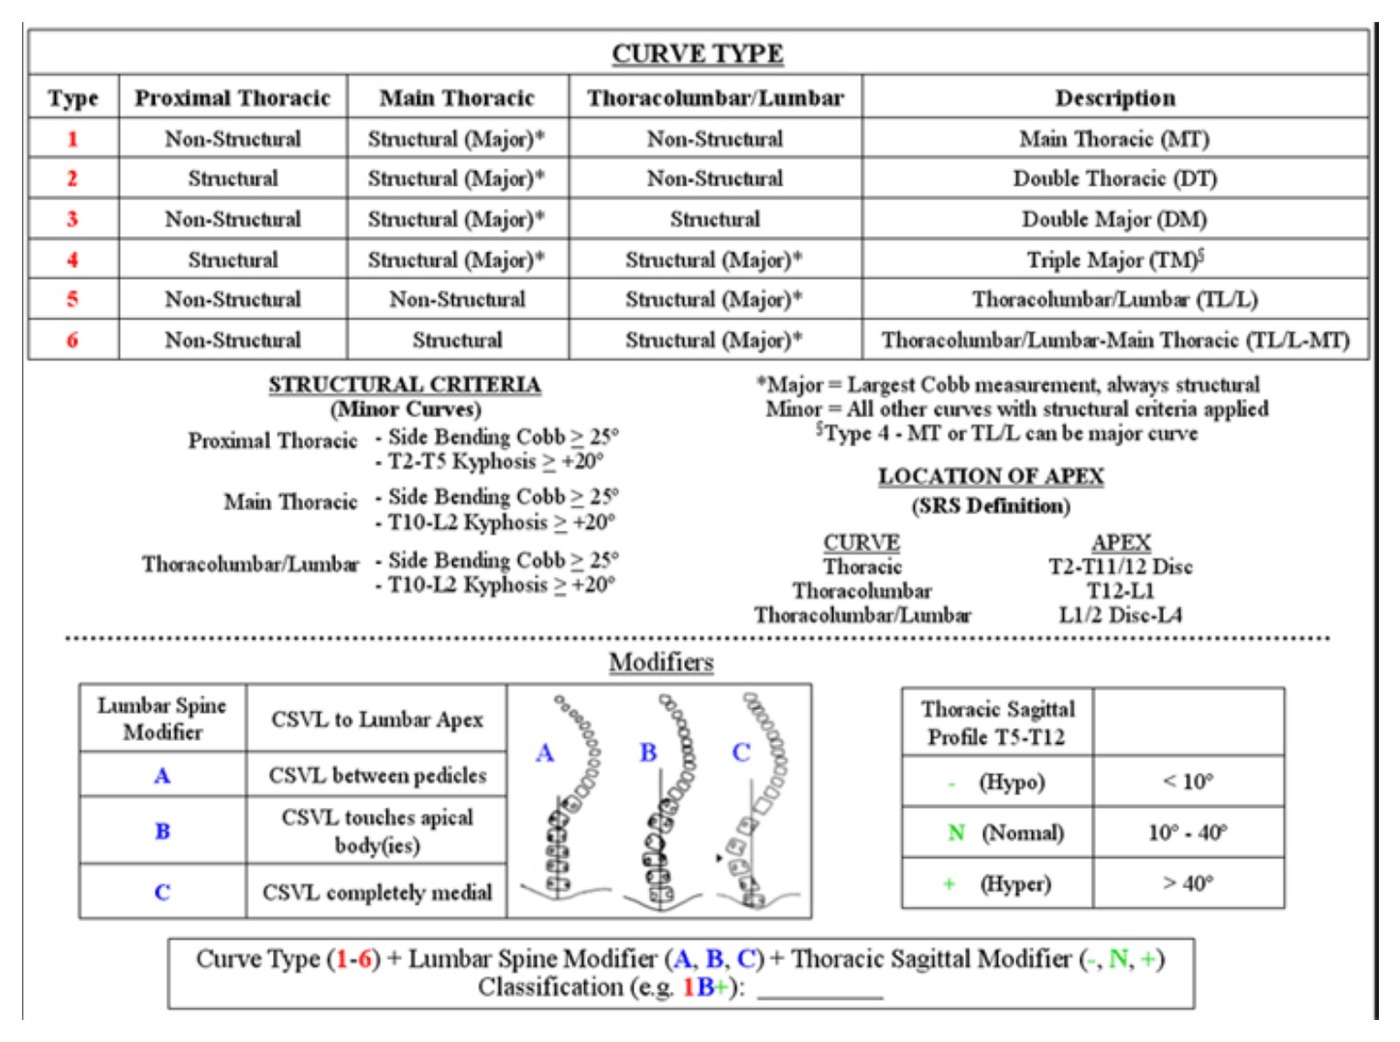
Classification / diagram
Fig 1. Classification / diagramtop left

Curve type:

•Main thoracic
•Double thoracic
•Double major
•Triple major
•Thoracolumbar-lumbar
•Thoracolumbar-lumbar, main thoracic
•Largest curve = major, always structural
•All other curves = minor, structural if side bending cobb >25deg (rigid)

Lumbar curve apex modifier:

Type / groupDefinition / note
ACSVL between pedicle
BCSVL outside of pedicle but still touching vertebrae
CCSVL medial to lumbar apex

Thoracic sagittal profile modifier:

•Hypo <10, normal 10-40, hyper >40
•*

Preop investigation for scoliosis surgery

•Side bending XR: Determine if minor curves are structural (Correct to <25deg with side bending)

Fulcrum bending XR: Determine correctability of curve

•CT for navigation
•MRI to rule out underlying structural abnormality (dural ectasia, spina bifida occulta)

Aim of surgery to achieve square fusion block

•<20deg tilt, <2cm truncal list
•Fuse all structural curve
•Classically fuse from end to end vertebrae

Direct Q&A

Q1 What operative steps, indications, and risks are listed for Preop investigation for scoliosis surgery?
•Side bending XR: Determine if minor curves are structural (Correct to <25deg with side bending)
Q2 What are the radiographic findings for Lenke classification?

CT for navigation

•MRI to rule out underlying structural abnormality (dural ectasia, spina bifida occulta)
Q3 What are the management aims for Lenke classification?
•<20deg tilt, <2cm truncal list
•Fuse all structural curve
•Classically fuse from end to end vertebrae

Raw speaker-note hierarchy audit

#lvlmarLindentlogicaloriginal note line
10NoneNone0Lenke classification
20NoneNone0Curve type:
31685800-2286002Main thoracic
41685800-2286002Double thoracic
51685800-2286002Double major
61685800-2286002Triple major
71685800-2286002Thoracolumbar-lumbar
81685800-2286002Thoracolumbar-lumbar, main thoracic
90NoneNone0Largest curve = major, always structural
100NoneNone0All other curves = minor, structural if side bending cobb >25deg (rigid)
110NoneNone0Lumbar curve apex modifier:
120NoneNone0A: CSVL between pedicle
130NoneNone0B: CSVL outside of pedicle but still touching vertebrae
140NoneNone0C: CSVL medial to lumbar apex
150NoneNone0Thoracic sagittal profile modifier:
160NoneNone0Hypo <10, normal 10-40, hyper >40
170NoneNone0*
180NoneNone0Preop investigation for scoliosis surgery
190171450-1714501Side bending XR: Determine if minor curves are structural (Correct to <25deg with side bending)
200171450-1714501Fulcrum bending XR: Determine correctability of curve
210171450-1714501CT for navigation
220171450-1714501MRI to rule out underlying structural abnormality (dural ectasia, spina bifida occulta)
230000Aim of surgery to achieve square fusion block
240000<20deg tilt, <2cm truncal list
250000Fuse all structural curve
260000Classically fuse from end to end vertebrae

Improved semantic hierarchy used for the study notes

#semantic levelsection?rewritten line
10yesLenke classification
20yesCurve type:
32Main thoracic
42Double thoracic
52Double major
62Triple major
72Thoracolumbar-lumbar
82Thoracolumbar-lumbar, main thoracic
91Largest curve = major, always structural
101All other curves = minor, structural if side bending cobb >25deg (rigid)
110yesLumbar curve apex modifier:
121A: CSVL between pedicle
131B: CSVL outside of pedicle but still touching vertebrae
141C: CSVL medial to lumbar apex
150yesThoracic sagittal profile modifier:
161Hypo <10, normal 10-40, hyper >40
171*
180yesPreop investigation for scoliosis surgery
191Side bending XR: Determine if minor curves are structural (Correct to <25deg with side bending)
200yesFulcrum bending XR: Determine correctability of curve
211CT for navigation
221MRI to rule out underlying structural abnormality (dural ectasia, spina bifida occulta)
230yesAim of surgery to achieve square fusion block
241<20deg tilt, <2cm truncal list
251Fuse all structural curve
261Classically fuse from end to end vertebrae