FRCS Paediatric Ortho — improved notes
FRCS Paediatric Ortho — visual inline notes

128. Galeazzi fracture

visual-inline rebuild1 extracted figuresspeaker notes XML32 study lines4 Q&A

Individual slide images have been cropped from the rendered slide and inserted beside the matching note section. The full slide remains below only for layout/audit.

Clean FRCS notes with inline figures

Radiographic description
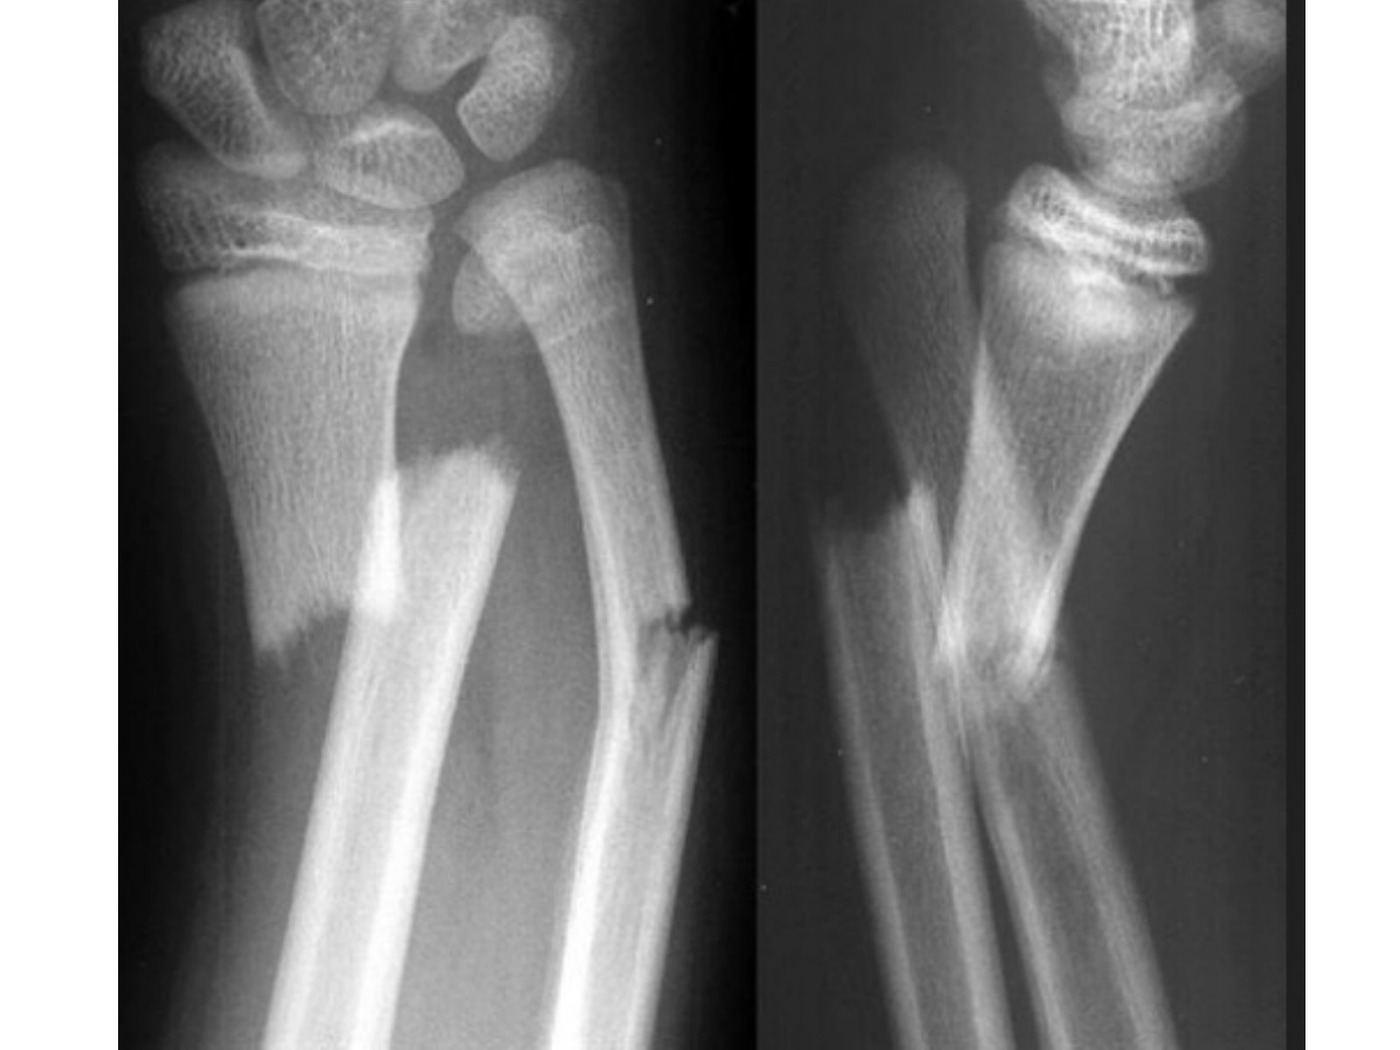
Radiograph / imaging
Fig 1. Radiograph / imagingtop left
•Displaced fracture distal shaft of radius+ greenstick fracture distal ulnar + fracture of distal ulna physis and DRUJ dislocation → Galeazzi fracture

Assessment:

•Age, mechanism of injury and r/o associated injury (Xray whole UL and look at PRUJ), NV injury, compartment syndrome

Aim of management:

•Restore full rotation of forearm
•Anatomical reduction of radius and concentric reduction of DRUJ

Initial mx:

•try CR + slab

Indications for surgery:

•Failed CR SHII
•SHIII/IV (unstable)
•Triplane variant
•Galeazzi

Technique:

•CR under GA
•Percut pinning with K wire x1 from radial styloid (needs to cross physis to be stable enough)
•Check DRUJ stability
•Method one: flex elbow to 90 deg, displacement in dorsal palmar direction with forearm in neutral, pronation, supination and with wrist with radial deviation
•Method two: compress the ulnar against the radius while the forearm is passively out through supination, pronation
•→ Stable = free mobilization
•Unstable in either pronation or supination = immobilize in stable position for 4-6 weeks
•Unstable in both pronation or supination (grossly unstable)
•Bone: check radius reduction, fix ulnar styloid if large fragment
•Soft tissue: open DRUJ to make sure not soft tissue interposition, TFCC repair
•If still unstable after addressing the above = transfix distal R and U proximal to DRUJ
•Long arm cast in supination
•May need ORIF – volar approach to radius, fix with IMN / plating

•Acceptable alignment in distal radius fracture
•<10yo: <30 deg
•>10yo: <20 deg

Direct Q&A

Q1 What are the radiographic findings for Galeazzi fracture?
•Displaced fracture distal shaft of radius+ greenstick fracture distal ulnar + fracture of distal ulna physis and DRUJ dislocation → Galeazzi fracture
Q2 What assessment points are listed for Galeazzi fracture?
•Age, mechanism of injury and r/o associated injury (Xray whole UL and look at PRUJ), NV injury, compartment syndrome
Q3 What are the management aims for Galeazzi fracture?

Restore full rotation of forearm

•Anatomical reduction of radius and concentric reduction of DRUJ
Q4 What operative steps, indications, and risks are listed for Indications for surgery?

Failed CR SHII

•SHIII/IV (unstable)
•Triplane variant
•Galeazzi

Raw speaker-note hierarchy audit

#lvlmarLindentlogicaloriginal note line
10NoneNone0Describe Xray:
20NoneNone0Displaced fracture distal shaft of radius+ greenstick fracture distal ulnar + fracture of distal ulna physis and DRUJ dislocation → Galeazzi fracture
30NoneNone0Assessment:
40NoneNone0Age, mechanism of injury and r/o associated injury (Xray whole UL and look at PRUJ), NV injury, compartment syndrome
50NoneNone0Aim of management:
60NoneNone0Restore full rotation of forearm
70NoneNone0Anatomical reduction of radius and concentric reduction of DRUJ
80NoneNone0Initial mx:
90000try CR + slab
100000Indications for surgery:
110171450-1714501Failed CR SHII
120171450-1714501SHIII/IV (unstable)
130171450-1714501Triplane variant
140171450-1714501Galeazzi
150000Technique:
160171450-1714501CR under GA
170171450-1714501Percut pinning with K wire x1 from radial styloid (needs to cross physis to be stable enough)
180171450-1714501Check DRUJ stability
191628650-1714502Method one: flex elbow to 90 deg, displacement in dorsal palmar direction with forearm in neutral, pronation, supination and with wrist with radial deviation
201628650-1714502Method two: compress the ulnar against the radius while the forearm is passively out through supination, pronation
21145720001→ Stable = free mobilization
221628650-1714502Unstable in either pronation or supination = immobilize in stable position for 4-6 weeks
231628650-1714502Unstable in both pronation or supination (grossly unstable)
2421085850-1714503Bone: check radius reduction, fix ulnar styloid if large fragment
2521085850-1714503Soft tissue: open DRUJ to make sure not soft tissue interposition, TFCC repair
2621085850-1714503If still unstable after addressing the above = transfix distal R and U proximal to DRUJ
270171450-1714501Long arm cast in supination
280171450-1714501May need ORIF – volar approach to radius, fix with IMN / plating
290000=============================
300000Acceptable alignment in distal radius fracture
310171450-1714501<10yo: <30 deg
320171450-1714501>10yo: <20 deg

Improved semantic hierarchy used for the study notes

#semantic levelsection?rewritten line
10yesRadiographic description
21Displaced fracture distal shaft of radius+ greenstick fracture distal ulnar + fracture of distal ulna physis and DRUJ dislocation → Galeazzi fracture
30yesAssessment:
41Age, mechanism of injury and r/o associated injury (Xray whole UL and look at PRUJ), NV injury, compartment syndrome
50yesAim of management:
61Restore full rotation of forearm
71Anatomical reduction of radius and concentric reduction of DRUJ
80yesInitial mx:
91try CR + slab
100yesIndications for surgery:
111Failed CR SHII
121SHIII/IV (unstable)
131Triplane variant
141Galeazzi
150yesTechnique:
161CR under GA
171Percut pinning with K wire x1 from radial styloid (needs to cross physis to be stable enough)
181Check DRUJ stability
192Method one: flex elbow to 90 deg, displacement in dorsal palmar direction with forearm in neutral, pronation, supination and with wrist with radial deviation
202Method two: compress the ulnar against the radius while the forearm is passively out through supination, pronation
211→ Stable = free mobilization
222Unstable in either pronation or supination = immobilize in stable position for 4-6 weeks
232Unstable in both pronation or supination (grossly unstable)
243Bone: check radius reduction, fix ulnar styloid if large fragment
253Soft tissue: open DRUJ to make sure not soft tissue interposition, TFCC repair
263If still unstable after addressing the above = transfix distal R and U proximal to DRUJ
271Long arm cast in supination
281May need ORIF – volar approach to radius, fix with IMN / plating
290——
301Acceptable alignment in distal radius fracture
311<10yo: <30 deg
321>10yo: <20 deg