FRCS Paediatric Ortho — improved notes
FRCS Paediatric Ortho — visual inline notes

139. Tillaux fracture

visual-inline rebuild1 extracted figuresspeaker notes XML12 study lines2 Q&A

Individual slide images have been cropped from the rendered slide and inserted beside the matching note section. The full slide remains below only for layout/audit.

Clean FRCS notes with inline figures

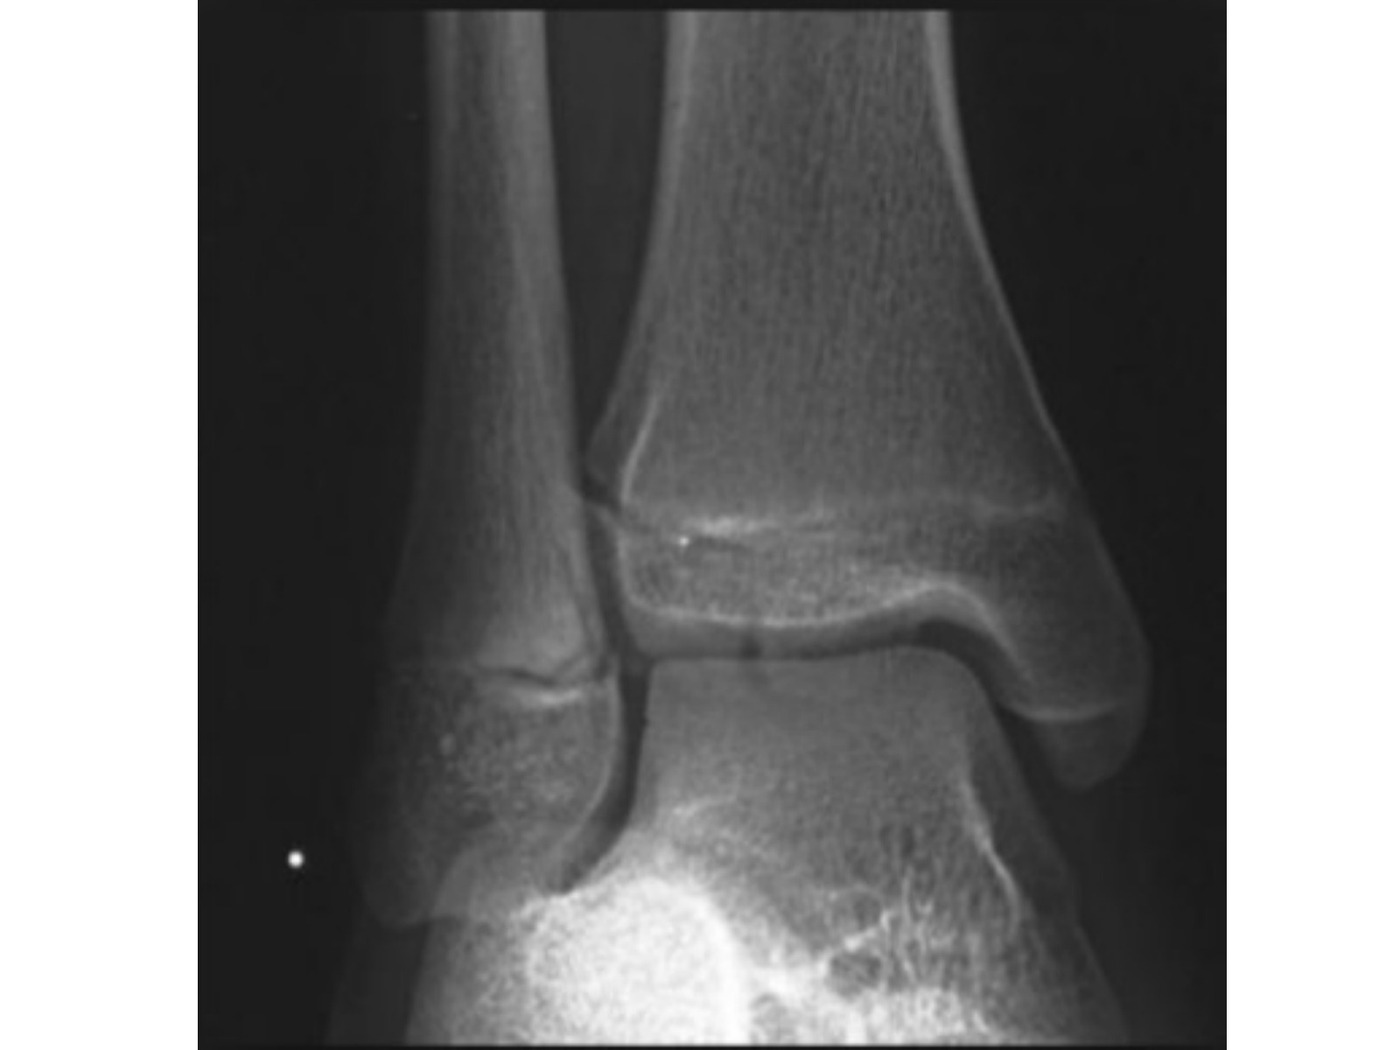
Ankle Xray of mortise view of skeletally immature patient
Radiograph / imaging
Fig 1. Radiograph / imagingtop left
•Fracture over distal tibia epiphysis on lateral side, fibula no fracture
•Tillaux fracture
•Which is an SH 3 Fracture
•Transitional fracture
•CT to delineate # pattern and see displacement
•Displacement <2mm conservative with long leg cast (for rotational control. Foot IR + direct anterior pressure + knee 30 deg flexion) x 4/52 then short leg cast x 2/52 (post cast CT to make sure no displacement)
•If displacement >2mm go for CR +/- OR via AL approach + stable fixation (percutaneous screw) (can be transphyseal as approaching skeletal maturity)
•Near end of growth, older than triplane ~ 12-14
•ER
•caused by an avulsion of the anterior inferior tibiofibular ligament
•Lack of fracture component in sagittal plane distinguish this fracture from triplane injury

Direct Q&A

Q1 What are the radiographic findings for Tillaux fracture?
•Fracture over distal tibia epiphysis on lateral side, fibula no fracture
•Tillaux fracture
•Which is an SH 3 Fracture
•Transitional fracture
•CT to delineate # pattern and see displacement
•Displacement <2mm conservative with long leg cast (for rotational control. Foot IR + direct anterior pressure + knee 30 deg flexion) x 4/52 then short leg cast x 2/52 (post cast CT to make sure no displacement)
•If displacement >2mm go for CR +/- OR via AL approach + stable fixation (percutaneous screw) (can be transphyseal as approaching skeletal maturity)
•Near end of growth, older than triplane ~ 12-14
•ER
•caused by an avulsion of the anterior inferior tibiofibular ligament
•Lack of fracture component in sagittal plane distinguish this fracture from triplane injury
Q2 How is Tillaux fracture managed?
•Displacement <2mm conservative with long leg cast (for rotational control. Foot IR + direct anterior pressure + knee 30 deg flexion) x 4/52 then short leg cast x 2/52 (post cast CT to make sure no displacement)
•If displacement >2mm go for CR +/- OR via AL approach + stable fixation (percutaneous screw) (can be transphyseal as approaching skeletal maturity)
•Near end of growth, older than triplane ~ 12-14
•ER
•caused by an avulsion of the anterior inferior tibiofibular ligament
•Lack of fracture component in sagittal plane distinguish this fracture from triplane injury

Raw speaker-note hierarchy audit

#lvlmarLindentlogicaloriginal note line
10NoneNone0Ankle Xray of mortise view of skeletally immature patient
20NoneNone0Fracture over distal tibia epiphysis on lateral side, fibula no fracture
30NoneNone0Tillaux fracture
40NoneNone0Which is an SH 3 Fracture
50NoneNone0Transitional fracture
60NoneNone0CT to delineate # pattern and see displacement
70NoneNone0Displacement <2mm conservative with long leg cast (for rotational control. Foot IR + direct anterior pressure + knee 30 deg flexion) x 4/52 then short leg cast x 2/52 (post cast CT to make sure no displacement)
80NoneNone0If displacement >2mm go for CR +/- OR via AL approach + stable fixation (percutaneous screw) (can be transphyseal as approaching skeletal maturity)
90NoneNone0Near end of growth, older than triplane ~ 12-14
100NoneNone0ER
110NoneNone0caused by an avulsion of the anterior inferior tibiofibular ligament
120NoneNone0Lack of fracture component in sagittal plane distinguish this fracture from triplane injury

Improved semantic hierarchy used for the study notes

#semantic levelsection?rewritten line
10Ankle Xray of mortise view of skeletally immature patient
21Fracture over distal tibia epiphysis on lateral side, fibula no fracture
31Tillaux fracture
41Which is an SH 3 Fracture
51Transitional fracture
61CT to delineate # pattern and see displacement
71Displacement <2mm conservative with long leg cast (for rotational control. Foot IR + direct anterior pressure + knee 30 deg flexion) x 4/52 then short leg cast x 2/52 (post cast CT to make sure no displacement)
81If displacement >2mm go for CR +/- OR via AL approach + stable fixation (percutaneous screw) (can be transphyseal as approaching skeletal maturity)
91Near end of growth, older than triplane ~ 12-14
101ER
111caused by an avulsion of the anterior inferior tibiofibular ligament
121Lack of fracture component in sagittal plane distinguish this fracture from triplane injury