FRCS Paediatric Ortho — improved notes
FRCS Paediatric Ortho — visual inline notes

014. Modified Dunn procedure for unstable severe SCFE

visual-inline rebuild1 extracted figuresspeaker notes XML9 study lines4 Q&A

Individual slide images have been cropped from the rendered slide and inserted beside the matching note section. The full slide remains below only for layout/audit.

Clean FRCS notes with inline figures

Modified Dunn procedure
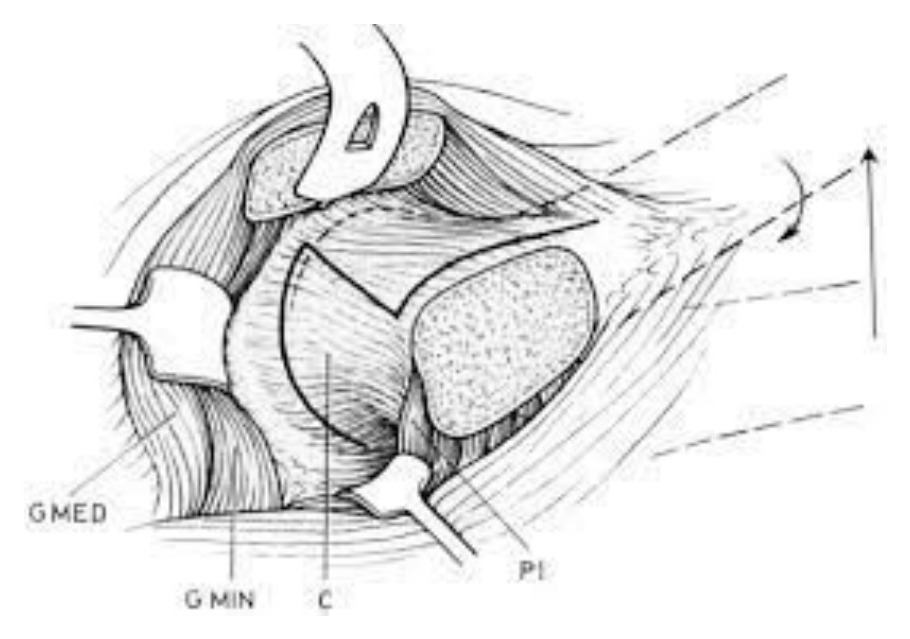
Operative / approach image - Modified Dunn operative diagram - visible label: Modified Dunn procedure
Fig 1. Operative / approach image - Modified Dunn operative diagram - visible label: Modified Dunn proceduremiddle left
•Done in elective setting

Approach

•Gibson interval (between Gmed and Glut max, c/f posterior approach with glut max splitting)
•(No need detach external rotators!)
•Troch flip osteotomy
•Z capsulotomy (from troch ridge to acetabulum along neck of femur, distal anterior towards calcar, parallel towards posterior
•Cut ligamentum teres → Flex + ER + add → anterior dislocation
•AVN up to 25% in inexp hands

Direct Q&A

Q1 What diagnostic or radiographic findings support Modified Dunn procedure for unstable severe SCFE?

Modified Dunn procedure

•Done in elective setting

Approach

•Gibson interval (between Gmed and Glut max, c/f posterior approach with glut max splitting)
•(No need detach external rotators!)
•Troch flip osteotomy
•Z capsulotomy (from troch ridge to acetabulum along neck of femur, distal anterior towards calcar, parallel towards posterior
•Cut ligamentum teres → Flex + ER + add → anterior dislocation
•AVN up to 25% in inexp hands
Q2 What operative steps, indications, and risks are listed for Modified Dunn procedure?

Done in elective setting

Q3 What operative steps, indications, and risks are listed for Approach?
•Gibson interval (between Gmed and Glut max, c/f posterior approach with glut max splitting)
•(No need detach external rotators!)
•Troch flip osteotomy
•Z capsulotomy (from troch ridge to acetabulum along neck of femur, distal anterior towards calcar, parallel towards posterior
•Cut ligamentum teres → Flex + ER + add → anterior dislocation
•AVN up to 25% in inexp hands
Q4 How is Modified Dunn procedure for unstable severe SCFE managed?

Modified Dunn procedure

•Done in elective setting

Approach

•Gibson interval (between Gmed and Glut max, c/f posterior approach with glut max splitting)
•(No need detach external rotators!)
•Troch flip osteotomy
•Z capsulotomy (from troch ridge to acetabulum along neck of femur, distal anterior towards calcar, parallel towards posterior
•Cut ligamentum teres → Flex + ER + add → anterior dislocation
•AVN up to 25% in inexp hands

Raw speaker-note hierarchy audit

#lvlmarLindentlogicaloriginal note line
10NoneNone0Modified Dunn procedure
20NoneNone0Done in elective setting
30NoneNone0Approach
40228600-2286001Gibson interval (between Gmed and Glut max, c/f posterior approach with glut max splitting)
50228600-2286001(No need detach external rotators!)
60228600-2286001Troch flip osteotomy
70228600-2286001Z capsulotomy (from troch ridge to acetabulum along neck of femur, distal anterior towards calcar, parallel towards posterior
80228600-2286001Cut ligamentum teres → Flex + ER + add → anterior dislocation
90000AVN up to 25% in inexp hands

Improved semantic hierarchy used for the study notes

#semantic levelsection?rewritten line
10Modified Dunn procedure
21Done in elective setting
30yesApproach
41Gibson interval (between Gmed and Glut max, c/f posterior approach with glut max splitting)
51(No need detach external rotators!)
61Troch flip osteotomy
71Z capsulotomy (from troch ridge to acetabulum along neck of femur, distal anterior towards calcar, parallel towards posterior
81Cut ligamentum teres → Flex + ER + add → anterior dislocation
91AVN up to 25% in inexp hands