Clean FRCS notes with inline figures
PFFD
•Proximal femoral focal deficiency
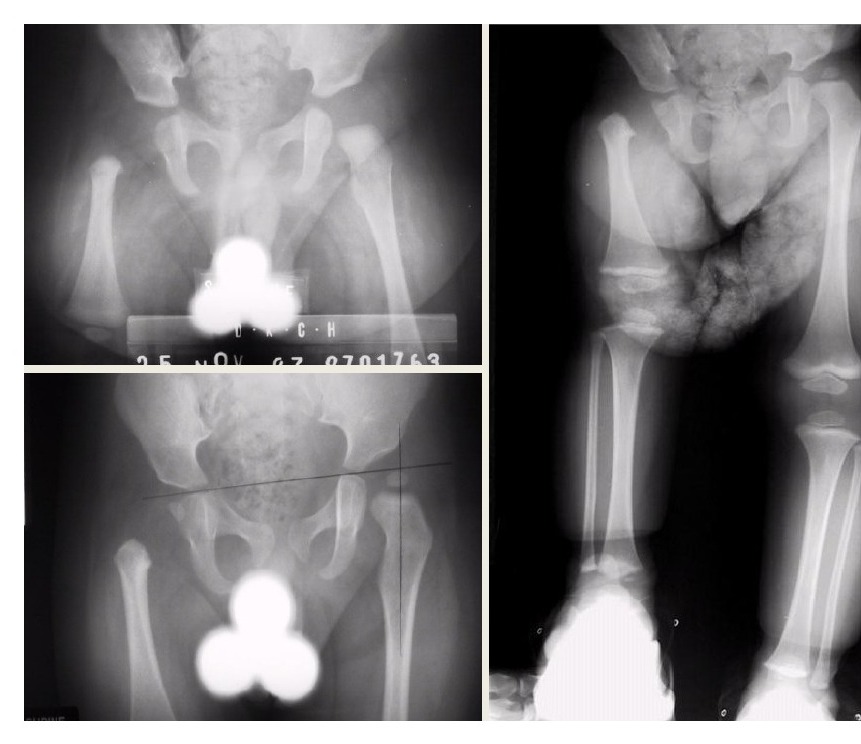
•Clinical photo of child with significant LLD
•Femurs appears short, flexed + abducted + ER (FABER)
•Knee + foot abnormalities
•Facial features (AD type)
•AP Xray pelvis with hip abnormalities + short femur + coxa vara
Epiphysis present?
•Acetabular (AI) / tear drop abnormalities
•Look for associated deformities (fibular hemimelia)
•Impression: PFFD, Aikten C, but need to have MRI to see if femoral ossification center is present
History
Birth history
•Maternal thalidomide
Examination
•Hip
•Knees stability
Foot functional?
•LLD (at least to mid tibia for it to be salvageable / reconstructable)
•MRI x assessment of development (any femoral head) and version
Management
•Treatment aim is to allow the patient to ambulate, whether this is through patient’s native limb or by prosthesis
•Factors to consider (LAF)
•LLD
Aitken classification (hip)
•Foot stability
•Conservative (SHOERAISE)
•First thing to determine is whether the LLD will be too significant for reconstructive procedures
•Predict LLD >20cm at maturity
•Foot to level of mid tibia
•Femur <50% of other leg
•If LLD not significant, then look to see if the hip is reconstructable.
Aitken classification
•A and B – femoral head present = reconstruct hip (valgus derotational osteotomy, PAO, ITB release, excise pseudoarthrosis + BG)
•C and D – femoral head absent – iliofemoral fusion
•Then followed by limb lengthening procedures
•If LLD significant, then the aim is for prosthesis fitting. See if foot is functional or not
•If functional, then iliofemoral fusion + van nes rotationoplasty
•If non functional, then knee fusion + syme amputation
•Aitken classification, A-D based on femoral and acetabular involvement
•AB femoral head +, CD femoral head -
•A→D head present, subtro pseudoarthrosis, absent head, absent head and proximal femur
•A→D Acetabular normal, mild dysplasia, severe dysplasia, abs
Lengthening timing
See LLD amount, ?need staged disease, how many times does it take?
•Roughly 1cm /month
•Consider psychological factors, roughly can start at 5y
Complication of lengthening
•Soft tissue: NV
•Bone: non union
•Joint: contracture
•General: infection
•Lengthening max 20-30%
Related to complications
What is the pathology?
•Sclerotome subtraction
Other classifications
Gillespie classification
•I congenital short femur (40-60%), functional hip and knee
•II true PFFD: defect + short, hip dysplasia, non functional knee
•Other associated anatomical anomalies
•Hip – coxa vara + retroversion, dysplasia
•Femur – PFFD
•Knee – LFC hypoplasia, genu valgus, patellar instability, cruciate insufficiency
•Tibia: Short + AM bowing
•Fib: fibular hemimelia
•Ankle: ankle valgus + ball and socket joint
•Foot: tarsal coalition, absent fib ray