Clean FRCS notes with inline figures
Fibrous dysplasia
Radiographic description
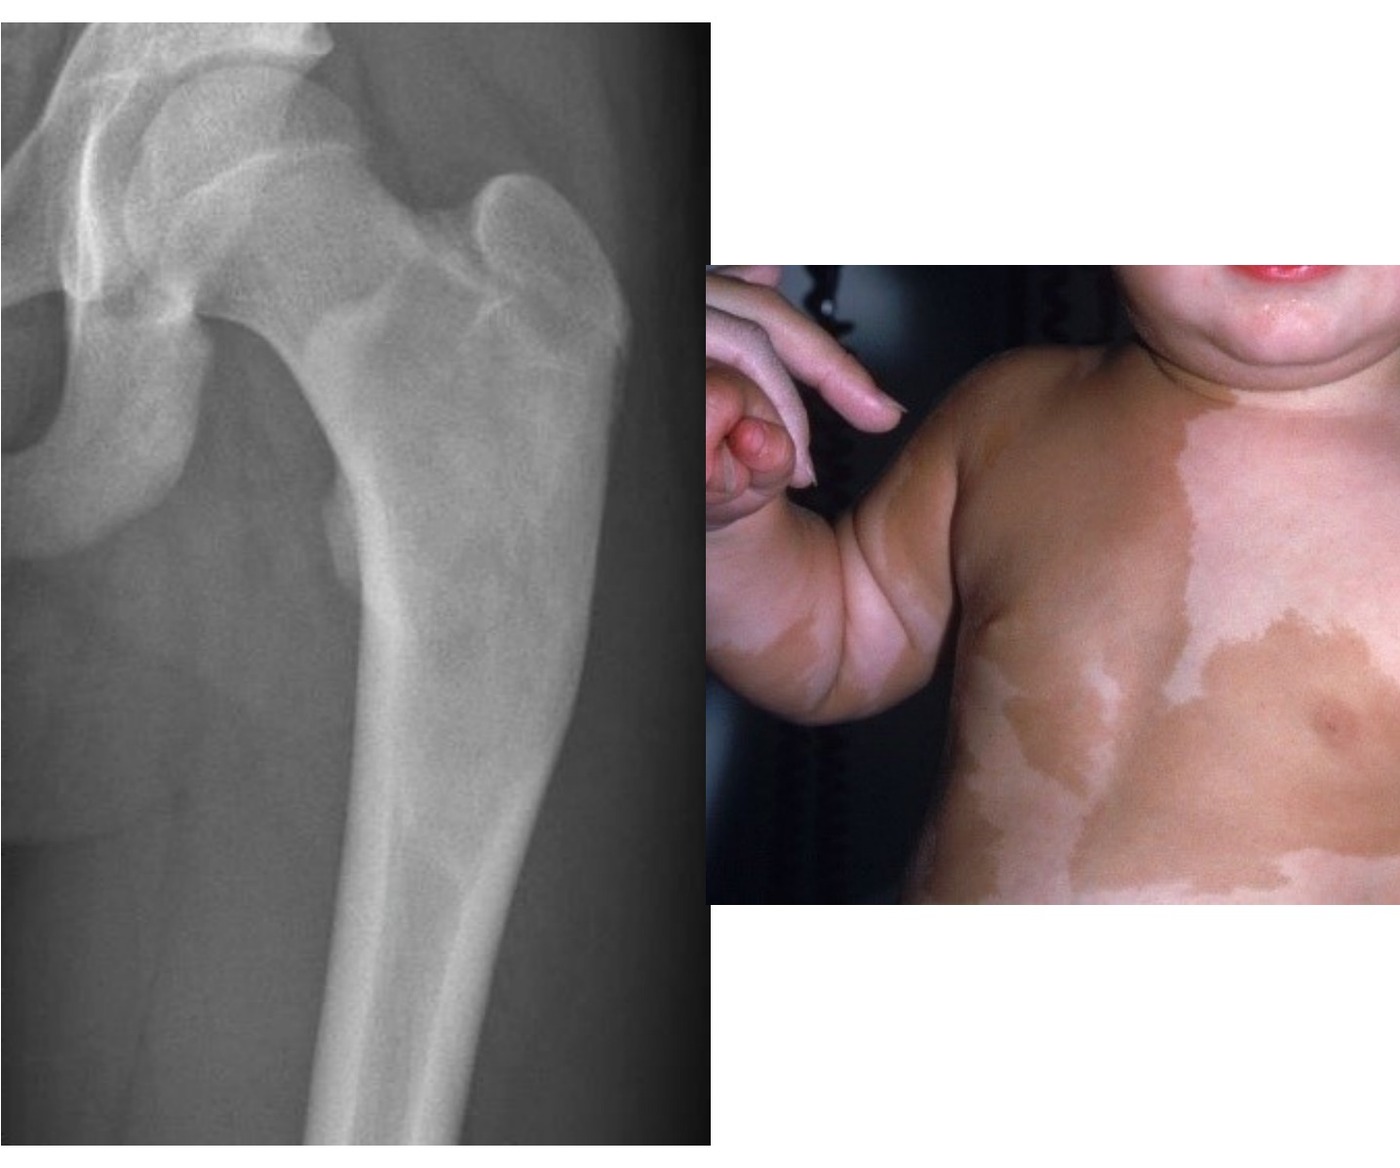
Expansile lesion at metaphyseal region of left femur with cortical thinning, intramedullary with narrow transitional zone, ground glass matrix, no periosteal reaction, mild varus deformity of proximal femur
•Fibrous dysplasia with shepherd crook deformity, Ddx: bone cyst/ enchondroma (if matrix less ground glass), infection, metabolic (brown’s tumour), haematological, metastasis in older age group
History
•Age+ premorbid
•Can involve any bone
•Female
•Current sx
•1. Pain
•Stress fracture → normal healing, but abnormal remodeling (similar to OI)
•Nocturnal pain → malignant transformation
•2. Deformity
•Mono vs polyostotic
•Coxa vara – Trendelenburg gait
•Blindness – Skull involvement
Associated:
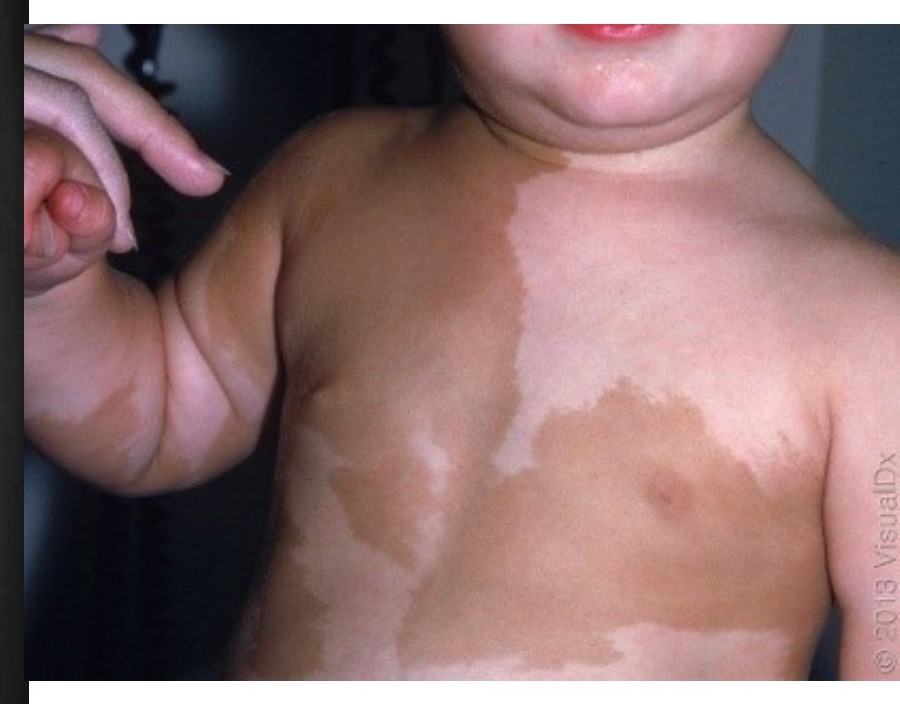
•McCune Albright syndrome
•Triad
•Polyostotic FD
•Café au lait spots with coast of Maine, stop at midline
•Hyperfunctioning endocrine – precocious puberty, hyperT4, acromegaly
•Scoliosis
•GNAS mutation
•2. Mazabraud syndrome
•Soft tissue intramuscular myxoma
Investigations
•Inflammatory markers, ALP, LDH → increase malignant transformation
•Skeletal survey to r/o polyostotic (if yes screen for syndrome), if mono-ostotic: consider biopsy for Dx
•Histology: Alphabet soup appearance: trabeculae of osteoid within fibrous stroma
Treatment:
Aim: decrease pain, prevent fracture +/- correct deformity
Counsel about natural history:
•Progression of existing lesion + appearance of new lesion
•Old lesion will not “mature”, problem of remodeling (decrease cellularity, increase collagen deposition, persistent woven bone, no compressive or tensile trabeculae, progressive deformity)
•Progressive deformity until maturity, but may progress again with maturity
•Medical
•Bisphosphonate for symptomatic polyostotic patient for pain relief, decrease fracture, partial resolution of lesion
•Denosumab – ongoing study, latest observational study in J bone min research 2021
•Surgical
Indication for OT:
•Pathological fracture
•Enlarging lesion
•Recurrent fracture, deformity
•High stress area (femoral neck)
Principle of OT:
•For polyostotic → mainly aimed at deformity correction and prevention of fracture
•For monostotic → aim to remove tumor i.e. curettage (curative)
•Curettage, allograft (autograft will be transformed into fibrous tissue), stable fixation with titanium IM nail
•+/- osteotomy for deformity correction
•Intraop difficulty? Prepare blood as lesions can be very vascular. Choose correct implant with right NSA
What is fibrous dysplasia?
•Localized dysfunction of osteoblast to differentiate (via increase in cAMP signaling) and mature causing failure of lamella bone formation. Bone replaced with fibrous tissue.
•Caused by mutation of Ch 20q23, not inherited
•Can be mono-ostotic / polyostotic (associated with McCune Albright syndrome)
•Can cause bone deformity, problem of remodeling
Malignant chance?
•1% (osteosarcoma/ fibrosarcoma) with poor prognosis, 5-10% in polyostotic