Clean FRCS notes with inline figures
Xray showing femur of skeletally immature patient
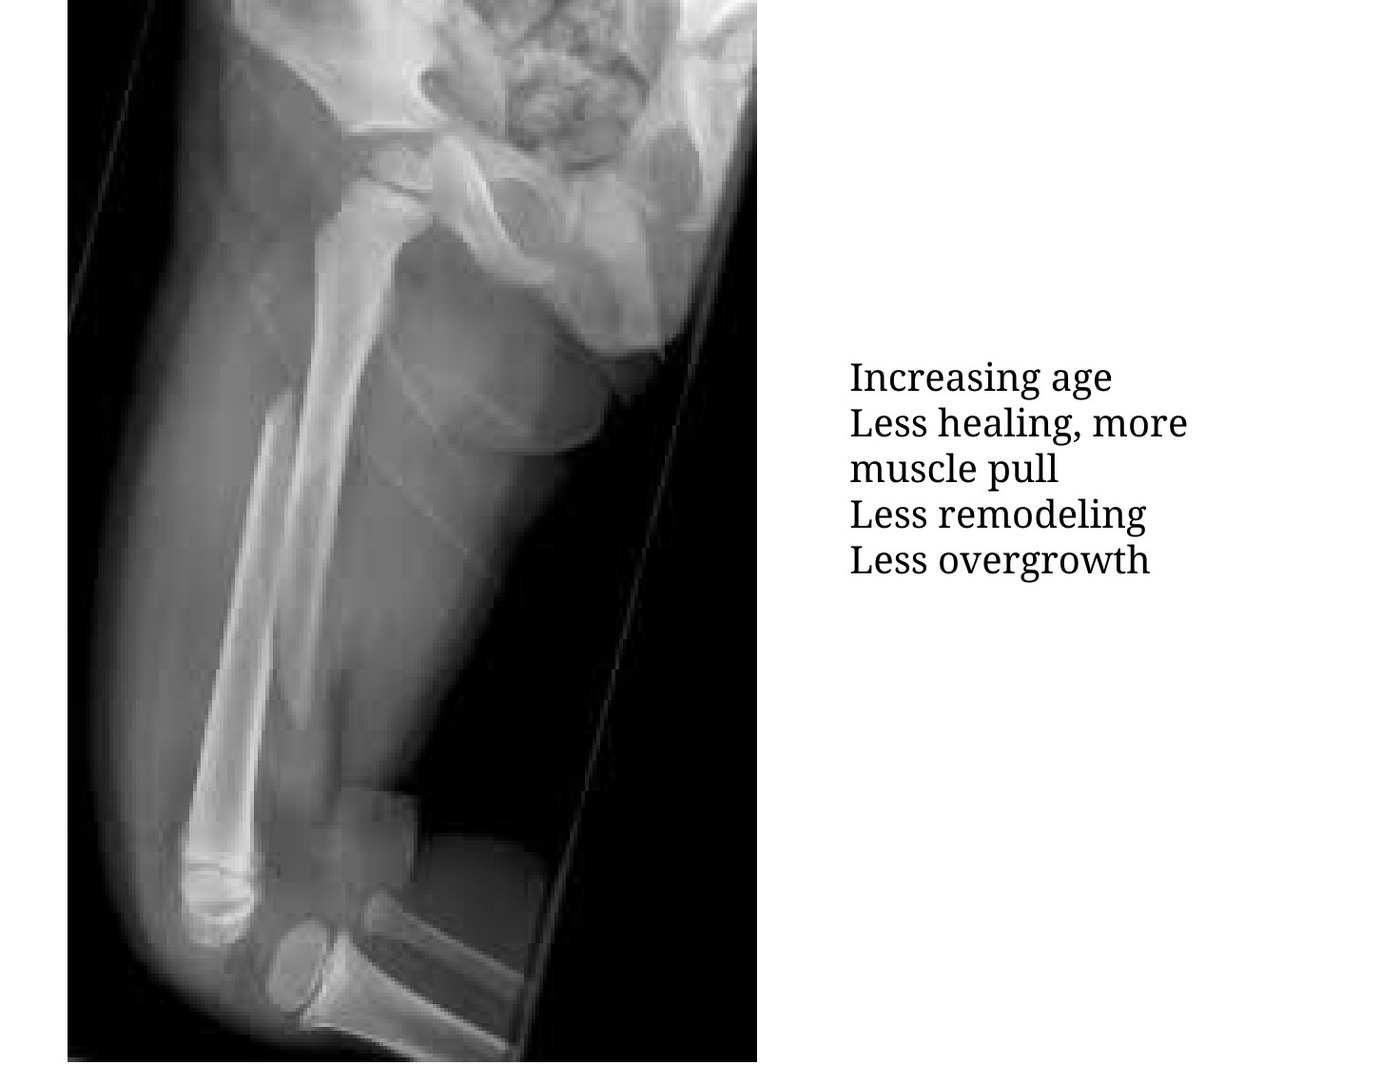
•Femoral fracture in mid shaft
•Spiral with no comminution, shortened with some rotational deformity, no valgus/ varus angulation deformity
Need lateral Xray to see AP angulation
•R/O NAI
Corroborate the history with other family members
•Observe interaction with others
Look for evidence of neglect
•Ask family history of skeletal dysplasia as a cause of bone fragility
Treatment depends on
•Patient: age, weight, underlying bone disease
•Disease: location, deformity, length stable – less relevant now with the advent of endcaps
•Acceptable deformity (Rockwood 2010)
•coronal sagittal shorten
•<2 30 30 20
•2-6 15 20 20
•6-11 10 15 15
•>11 5 10 10
•Will overgrow ~1.5cm, static 2yrs from injury (Shapiro 3)
Treatment:
•<6m PH
•6m – 6y Gallow traction if needed then hip spica up to 8 weeks [surgery in the form of exfix/elastic nail (>7mm IM canal) if alignment unacceptable, open fracture or polytrauma]
•6y-10y flexible nail 1. not very prox or very distal, 2. length unstable (only relative because of endcaps), otherwise exfix or submuscular plate
•>10 or >100lb or length unstable: submuscular bridging plating/ [adolescent lateral entry] nailing (piriformis entry will injure medial circumflex artery → AVN) GT entry (cause epiphysiodesis) ok if > 10y
Bryant / Gallow traction:
Indication: shortening >3cm + decide for cast
Technique:
•Overhead skin traction
•Knees in full extension
•5-10lbs (just enough to lift buttock off the mattress)
Till sticky callus seen on XR ~2/52 (16-18kg)
•Then change to hip spica
•HIP SPICA
•**Never traction during casting, muscle contraction after GA will cause compartment syndrome**
•Quad contract → femur shorten again → cast impinge on posterior leg → compartment
•Do hip spica after Gallow traction 1 wk to improve length
•After traction and callus formed
•Age + 3week / most 8weeks
Weekly Xray in first 3 weeks
How to apply a hip spica?
•Place child on spica table
•Long leg cast applied with knee in 90 deg flexion, with generous padding over foot popliteal fossa to prevent injury to popliteal vessels and peroneal nerve
•Three point molding centered at fracture site
•Proximal: may need ORIF due to strong muscle pull
•Middle: valgus molding for varus displacement
•Distal: flex knee 20deg to reduce pull of gastro
•Place folded towel on anterior thorax and abdomen to create space for inspiration
•Apply 2 layers of stockingnette followed by cotton (Velband) or gortex material over trunk
•Apply a thick belt of felt across the chest just below nipple line, and a second felt belt over sacrum, PSIS and ASIS
Double check reduction on XR
•Apply one and half leg spica cast with hip flexed to 90 degrees, 30 degrees of abduction (E: neutral rotation) (human position), and connect with long leg cast [vs 6-18m DDH F100 Abd 50]
•Why this position? Deforming force same as adult
•Reinforce with broomstick between thighs
•Perineal window
•FU weekly for first 3 weeks, duration = age + 3 weeks, up to 8 weeks
•Are you aware of any evidence regarding mx of femur fractures in 4-10 yrs
•Wright et al Lancet 2005 RCT
•Malunion rates after exfix vs flexible IM nails
•Improved outcomes with flexible IM nail
•AAOS guidelines – do no advocate routine use of exfix in younger children