Clean FRCS notes with inline figures
•Xray showing tibial eminence fracture, displaced, no hinge in skeletally immature patient
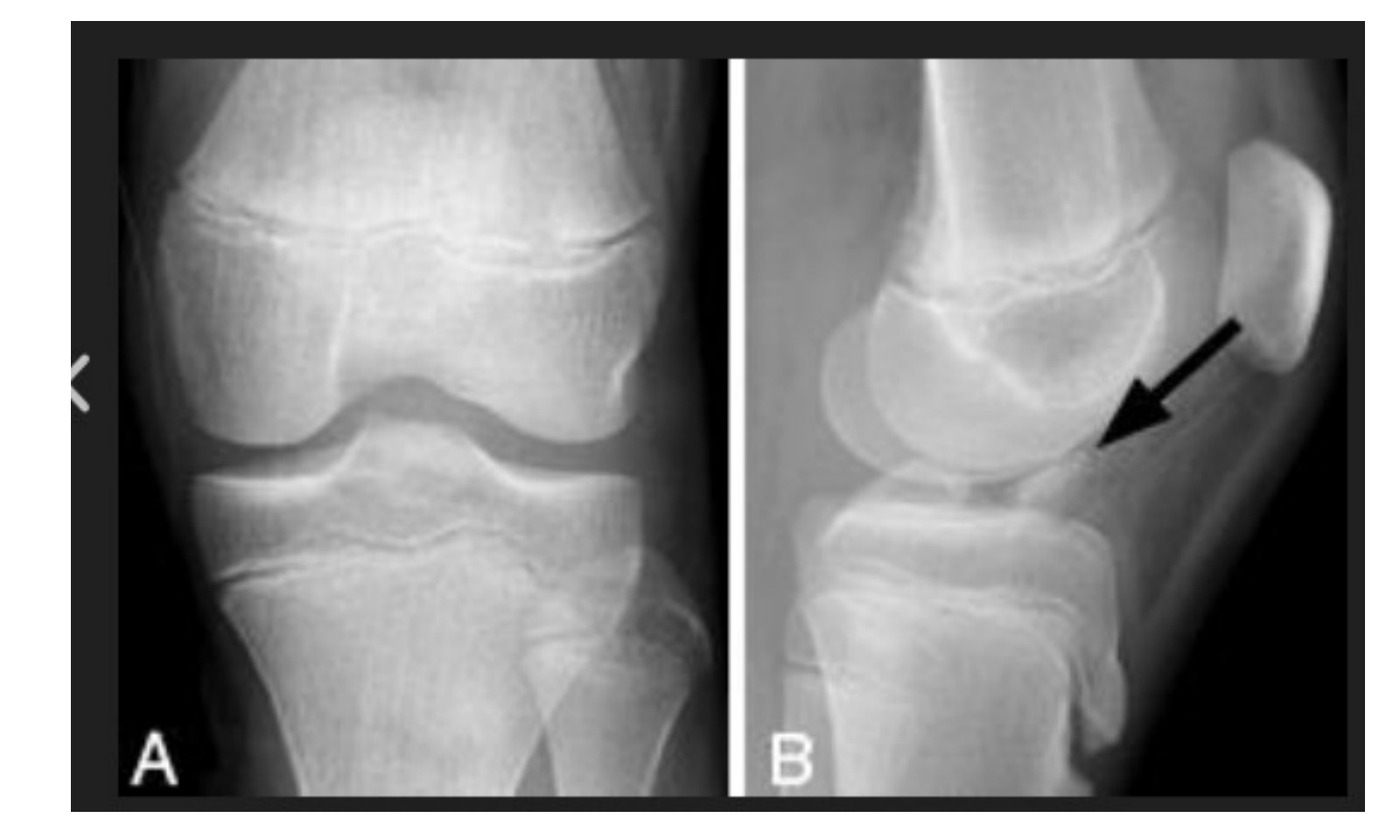
•ACL avulsion fracture
Meyers and McKeever classification
•1 undisplaced (<3mm)
•2 hinged
•3 displaced
•4 displaced + comminuted
•Clinically look for open wound, rule out other injuries
•Association(40%)
•meniscal injury
•collateral ligament injury
•capsular damage
•OC fracture
•MRI to rule out associated injuries, look for interposed meniscus, intermeniscal ligament → need OT
•Open/ arthroscopic reduction and fixation
•Young with pin / pullout suture, old with screw
•(common mechanism is hyperextension, 8-14y)
•Type 1, reducible Type 2: immobilize at 20deg
•CR in type II before casting by hyperextension to reduce
•Cast in 20deg flexion to minimize distraction forces
Indication x OT
•Type 3, 4
•Mechanical block
•Entrapped soft tissue
•Other injuries
Procedure:
•Supine + tourniquet
•AM and AL portal
•Diagnostic scope
•Debride hematoma + interposed meniscus + intermeniscal ligament
•2 strand repair with nonabsorbable sutures, wrap around midsubstance of ACL
•Drill hole with ACL tibial jig
•Before closing, need to make sure there is no impingement at full extension